

Today’s warning that up to 20 maternity units in England may need to close or change how they operate highlights the risks of addressing staffing shortages by removing access to local maternity care. Speaking to The Guardian, Matthew Hopkins, NHS Alliance’s director for acute care, argued that concentrating births in fewer, better-staffed hospitals may be necessary amid shortages of obstetric doctors and rising caesarean section rates.
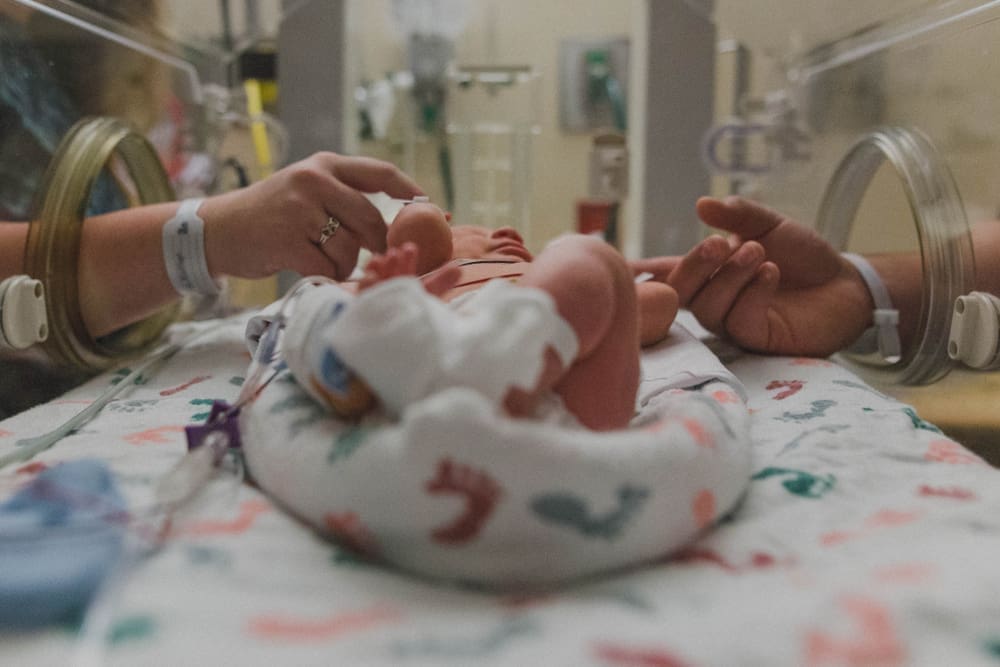
His patient-safety concerns are justified. Keeping an obstetric unit open without sufficient specialist doctors can be dangerous, particularly when complications arise during labour and emergency intervention is needed. However, closing local maternity services creates other risks, especially for women who must travel much farther to receive urgent care.
The consequences are already being felt in North Devon, where births at North Devon District Hospital have been suspended since August because of staffing shortages. Its latest readiness assessment confirmed that services would remain suspended, with no reopening date. Since the suspension began, the Daily Mirror has reported five babies being born in ambulances, A&E departments and hospital reception areas. While the trust has reported no confirmed safety incidents related to the suspension, these reports highlight the circumstances families must prepare for without their local birthing unit.
Through my work representing families affected by maternity negligence, I have seen how quickly complications can develop and the devastating consequences that delays in assessment and treatment can have. Women can require urgent maternity assessment at any stage of pregnancy, and having to travel further to hospital could delay treatment when complications arise. In North Devon, the journey from Barnstaple to Exeter is around 43 miles. For women experiencing complications, that journey could mean a dangerous delay in receiving emergency treatment.
Hopkins has raised an important point about the increasing demand for caesarean sections, which accounted for 45% of births in England last year, compared with 33% in 2020. The MBRRACE-UK findings highlighted by The Guardian identified cases where delays in accessing an obstetric surgeon or operating theatre contributed to maternal deaths. Maternity units clearly need reliable access to specialist doctors and facilities, but larger hospitals must have the capacity to accommodate additional births safely before more services are transferred to them.
There is a wider workforce problem that can’t be ignored. The Royal College of Obstetricians and Gynaecologists’ latest workforce census found that nearly one in five respondents intended to leave the specialty within five years. Smaller hospitals still require sufficient obstetric cover to manage emergencies, despite delivering fewer babies, and rural locations can face recruitment difficulties. Yet the government confirmed in June that it does not centrally hold figures on temporary maternity closures caused by staffing shortages. Without this information, it is harder to assess how widespread the problem is and identify services that may need urgent support.
The National Maternity and Neonatal Taskforce should examine which units are vulnerable to staffing shortages and what can be done to maintain safe local services before emergency suspensions become necessary. Last week, families in North Devon petitioned Parliament for stronger maternity staffing and national action to prevent further emergency suspensions, warning of the risks posed by lengthy journeys to alternative hospitals. When suspensions cannot be avoided, families need clear explanations of why services have closed, reliable arrangements for urgent care and regular updates on when they might reopen. Women should not be left unsure where to turn if complications arise during pregnancy or labour.
Closing maternity units should be a last resort, with every effort made to address staffing shortages before withdrawing services. The government and National Maternity and Neonatal Taskforce must act now to identify and support units at risk of closure as early as possible to help prevent further suspensions. Any proposed closures must be backed by clear evidence that alternative arrangements will be safer for mothers and babies, particularly those facing longer journeys to hospital.





